Key takeaways
- Progesterone decline often begins 5-10 years before menopause and is the primary driver of early perimenopausal insomnia.
- Bioidentical micronized progesterone metabolizes into allopregnanolone, providing natural anxiolytic and sleep-inducing effects.
- Synthetic progestins (e.g., medroxyprogesterone) lack progesterone's GABA-mediated neurosteroid action and carry distinct risk profiles.
- Combining evening progesterone with GABA-supporting nutrients (Magnesium Glycinate 400mg, Apigenin 50mg) optimizes night recovery.
Medical disclaimer: Content is for informational purposes and does not replace medical advice.
Why Does Progesterone Drop First in Perimenopause?
During peak reproductive years, progesterone is produced primarily by the corpus luteum in the ovary following each ovulation. As women enter their 40s, ovarian follicles become less responsive, leading to frequent anovulatory cycles (cycles without ovulation). Without ovulation, no corpus luteum forms — resulting in zero luteal phase progesterone production. PMID 21757538
This creates a state of relative 'estrogen dominance,' where estrogen continues to be secreted (often in irregular surges) while balancing, calming progesterone drops near zero. This absence is rapidly felt in the central nervous system as heightened stress reactivity, night sweats, and pronounced difficulty falling asleep or staying asleep through the night. PMID 21757538
The hormonal imbalance is exacerbated because progesterone itself serves as an upstream precursor for downstream neurosteroids and adrenal hormones. When chronic physiological or psychological stress prompts the adrenal cortex to prioritize cortisol synthesis, reproductive steroid pathways are further suppressed. This amplifies the vicious cycle of fragmented night sleep, elevated morning exhaustion, and decreased emotional resilience. PMID 21757538
For women in their 40s, sleep disturbances often precede irregular menstrual cycles or vasomotor hot flashes by several years. Recognizing early progesterone decline and understanding its neurochemical impact is therefore essential for preserving cognitive clarity, metabolic homeostasis, and long-term vitality. PMID 21757538
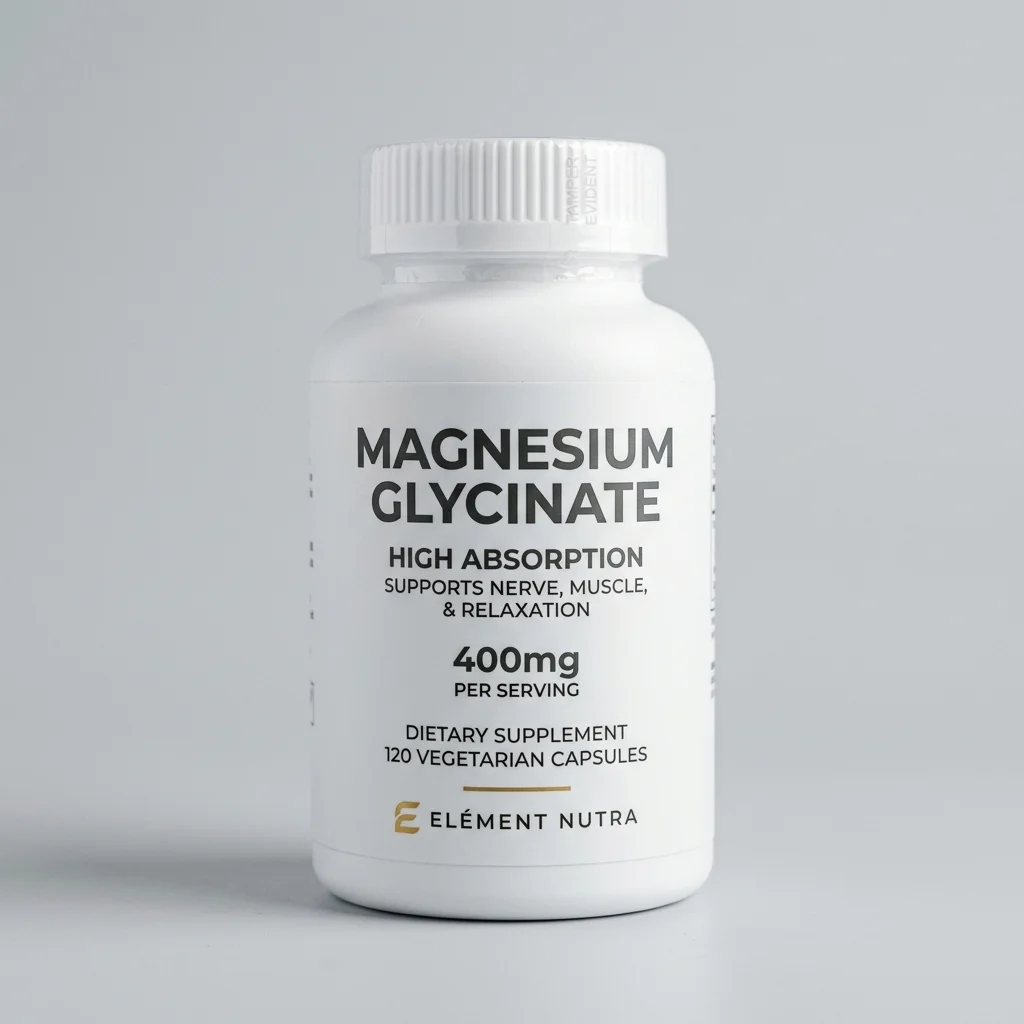
Magnesium Glycinate 400mg Capsules
Highly bioavailable chelated magnesium bound to glycine for maximum sleep and muscle absorption.
- Activates central GABA receptors for deep sleep
- Gentle on the stomach with superior bioavailability
Progesterone's Neurosteroid Mechanism: Allopregnanolone and GABA
Progesterone is far more than a reproductive hormone; it is a potent neurosteroid. When oral micronized progesterone is taken at bedtime, it undergoes hepatic and neural metabolism into allopregnanolone. Allopregnanolone acts as a potent positive allosteric modulator of GABA-A receptors — the exact neural receptors targeted by endogenous calming neurotransmitters. PMID 26657287 PMID 28438640
Crucially, allopregnanolone enhances natural physiological sleep architecture. Clinical polysomnography studies show that oral micronized progesterone (100-200 mg at bedtime) increases deep slow-wave sleep (Stage N3) duration without suppressing REM sleep or causing morning hangover effects. Furthermore, progesterone dampens hypothalamic thermoregulation, reducing nighttime hot flashes and nocturnal awakenings. PMID 26657287 PMID 28438640
Unlike conventional hypnotic sedatives (such as benzodiazepines and Z-drugs), which distort normal sleep architecture and carry dependency risks, bioidentical progesterone restores the brain's natural inhibitory neurotransmitter tone. The central nervous system preserves its physiological sleep cycles, facilitating glymphatic cerebrospinal clearance and nocturnal memory consolidation. PMID 26657287 PMID 28438640
Bioidentical Progesterone vs. Synthetic Progestins & Synergistic Nutrients
It is essential to distinguish bioidentical micronized progesterone (moleculary identical to endogenous progesterone, e.g., Utrogestan or Prometrium) from synthetic progestins (e.g., medroxyprogesterone acetate or norethindrone). Synthetic progestins do not metabolize into allopregnanolone and therefore fail to exert calming GABAergic effects on sleep; in fact, clinical trials link progestins to mood disruptions and altered cardiovascular markers. PMID 22978257 PMID 33865376
For women in perimenopause seeking to optimize sleep naturally or alongside HRT, targeted nutritional support offers powerful synergy. Combining Magnesium Glycinate (400 mg chelated magnesium bound to the GABA agonist glycine) with Apigenin (50 mg bioflavonoid from chamomile) reinforces allopregnanolone's action on GABA receptors, encouraging deep uninterrupted sleep. PMID 22978257 PMID 33865376
Prescription bioidentical progesterone should always be discussed with a qualified physician or gynecologist, particularly when co-administered with estrogen to protect the endometrial lining. PMID 22978257 PMID 33865376
Internal Further Reading
Read also in the same cluster

Apigenin 50mg Capsules
Pure apigenin bioflavonoid extracted from chamomile for natural GABA-A receptor activation and calm before sleep.
- Binds to central GABA-A receptors without dependence
- Synergistic with magnesium glycinate for deep sleep
FAQ
Why does progesterone deficiency disrupt sleep in your 40s?
Progesterone metabolizes in the brain into allopregnanolone, which activates GABA receptors. As progesterone drops in perimenopause, the brain loses its primary natural calming agent.
What is the difference between bioidentical progesterone and synthetic progestins?
Bioidentical progesterone is 100% identical to human progesterone and forms sleep-inducing allopregnanolone, whereas synthetic progestins have a different chemical structure and lack GABA-calming benefits.
Which supplements pair well with progesterone for sleep?
Magnesium Glycinate (400 mg) and Apigenin (50 mg) act synergistically on GABA receptors to deepen slow-wave sleep.
Sources and References
- [1]
- [2]
- [3]
- [4]
Show all 5 sources (1 more)
- [5]
Editorial History
27. juli 2026
Første publicering
Første version blev publiceret som del af healthy aging med intro, takeaways, FAQ og referenceblok.
27. juli 2026
Faglig gennemgang
Formuleringer, forbehold og interne links blev gennemgået for klarhed, konsistens og YMYL-tydelighed.
27. juli 2026
Seneste opdatering
Bioidentical Progesterone & Sleep (2026) fik opdaterede metadata, referenceoutput og forbedret beslutningsnær struktur.

Medical Review
Medical Review and Update Process
This article has been medically reviewed by Vadim Doroshenko with a focus on clinical accuracy, sources, disclaimers, and whether the conclusions still align with current scientific evidence.

Editorial Profile
Borys Viktorovytj Riabtsev
Borys Viktorovytj Riabtsev publishes Longevity Lab as a research-backed information project on precision medicine, metabolic health, and healthy aging, utilizing rigorous sources, independent medical review, and objective YMYL communication.